September 23, 2026; By rarebluemoon
For most of the last decade, the conversation about stellate ganglion block went like this. Veterans and first responders reported dramatic relief. Skeptics pointed out that anecdotes are not evidence. Both sides were right, and the argument went nowhere.
That has changed. There is now randomized, sham-controlled, multisite evidence, a published meta-analysis, and a large clinical series with standardized before-and-after measurement. The picture that emerges is genuinely encouraging, and it is worth laying out for patients who have been hearing about this procedure without knowing what stands behind it.
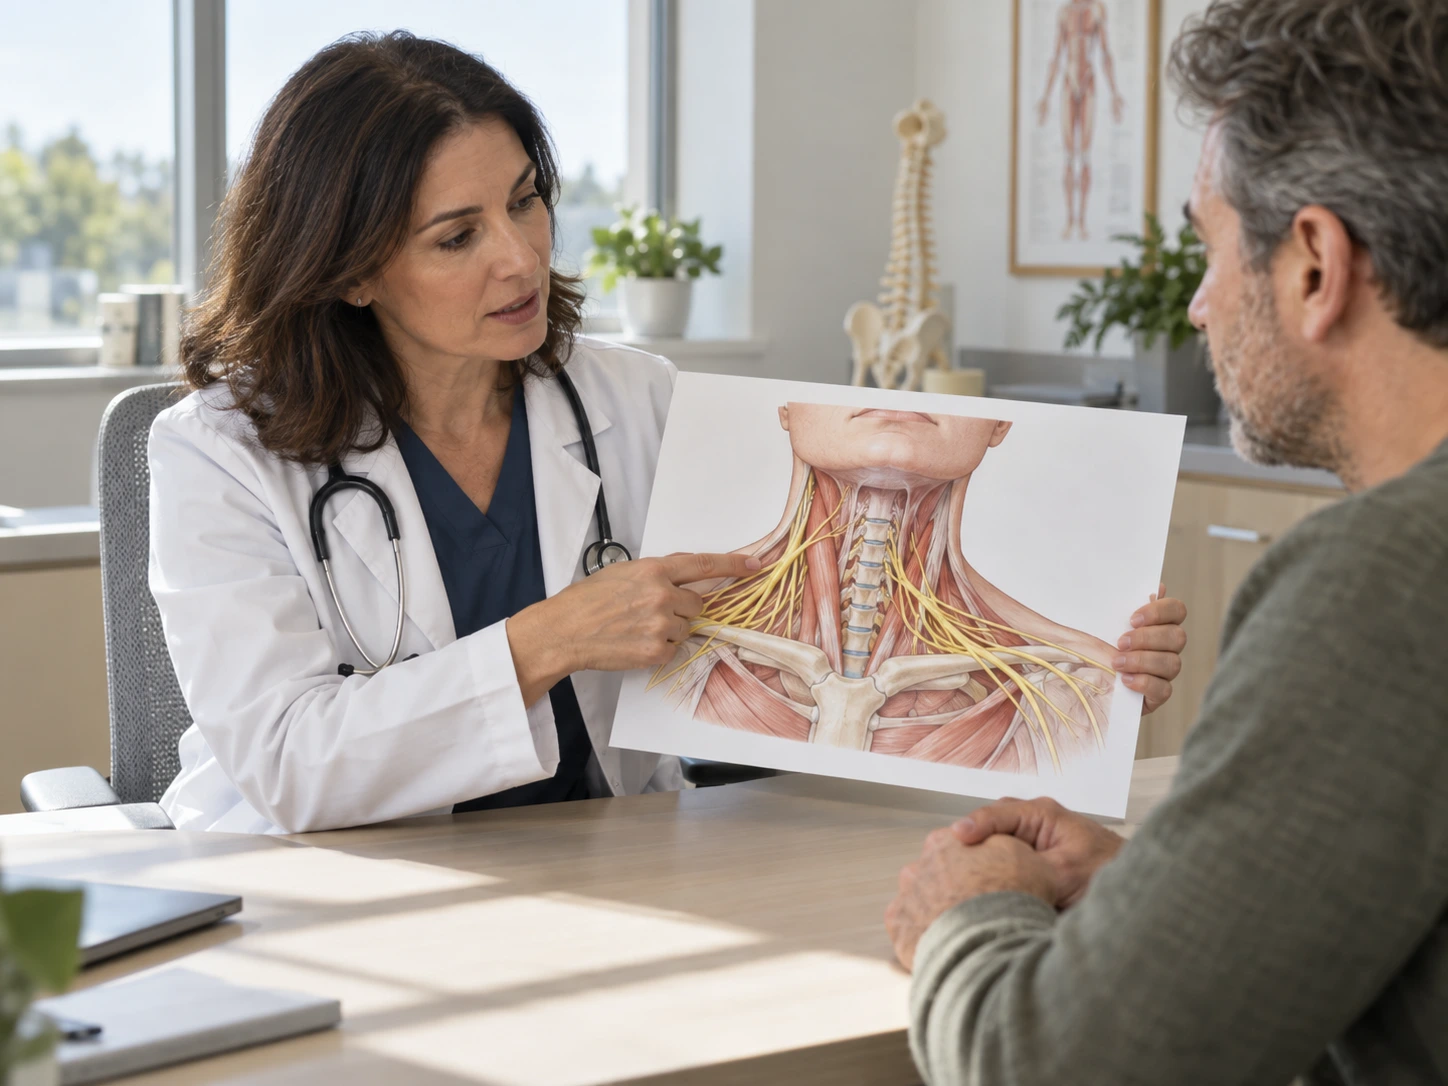
The stellate ganglion is a cluster of sympathetic nerve tissue near the base of the neck. The sympathetic branch of the autonomic nervous system runs the fight-or-flight response, the machinery that operates without you deciding anything: heart rate, vigilance, startle, the physical sense of being braced for something.
In trauma-related conditions, that machinery often behaves as though the threat never ended. The working model behind SGB is that a local anesthetic placed near the ganglion interrupts that signaling long enough for the system to settle into a different pattern.
The injection is brief and performed under image guidance, which is the modern standard for accurate needle placement. A successful block is confirmed by a temporary drooping of the eyelid and constriction of the pupil on that side, appearing within about fifteen minutes. Patients are awake throughout. The anesthetics used are long-established drugs, and their use for trauma-related symptoms is off-label, meaning the FDA has not evaluated them specifically for this purpose. That is common in medicine and worth knowing.
The strongest single piece of evidence came in 2020 in JAMA Psychiatry. It was the first multisite randomized trial of SGB for PTSD, conducted across three Army Interdisciplinary Pain Management Centers, with 113 active-duty service members randomized two-to-one to SGB or a sham procedure. Participants and assessors were both blinded.
Patients received two blocks, at baseline and two weeks. At eight weeks, the SGB group improved by a mean of 12.6 points on the CAPS-5 scale against 6.1 points in the sham group.
CAPS-5 is the clinician-administered standard for PTSD symptom severity, scored 0 to 80. The reduction in the SGB group falls inside the range commonly cited as clinically meaningful, roughly 10 to 15 points, while the sham group’s did not reach it. And the comparison was against a sham procedure rather than a waitlist, which is a considerably harder benchmark to beat.
A systematic review and meta-analysis published in 2025 searched seven databases through November 2024 and pooled the available controlled data. The pooled mean difference in CAPS scores favored SGB by 6.24 points against control, statistically significant at p equals 0.006 in a random-effects model. The authors rated the methodological quality of the included randomized trials as high. Two randomized trials and one case-control study met inclusion, so this is a small pooled body rather than a large one.
The included body of evidence is still small, and the authors say so. But pooling is where early positive results either survive or evaporate, and this one survived.
Trials tell you about averages under controlled conditions. Clinical series tell you what happens in practice.
In 2023, a series of 285 patients tracked GAD-7 anxiety scores before the procedure and again at one week and one month. Mean baseline was 15.9, in the severe range. Scores dropped 9.0 points at one week, with about 80 percent of those assessed showing clinically meaningful improvement, and the gain largely held at one month, when roughly 75 percent still met that threshold.
Effect sizes in that range are uncommon in this area of medicine.
Two honest caveats. There was no control group, so some of that change reflects the natural course and the effect of receiving attentive care. And the authors practice at a clinic specializing in this procedure, which is worth knowing when reading any clinical series. Neither caveat erases a result of that magnitude in that many patients.
For completeness, because you may encounter it: a trial published in 2016 randomized 42 military participants and found no difference between SGB and sham.
The VA’s own evidence review rated that trial fair quality and catalogued why. Overall attrition reached 57 percent and ran higher in the SGB arm. The anesthetic dose was 5 cc rather than the 7 cc used in prior work, with no stated rationale. Needle placement targeted C5 to C6, while the stellate ganglion typically sits at C6 to C7, so it is unclear the injection reached the target in every patient. And the saline sham was likely a weak blind, since an actual block produces a visible drooping eyelid that patients can notice.
I mention all of this because a clinic that hides the negative study is a clinic you should not trust. But the reasons that trial came out flat are documented, and the larger multisite work that followed was designed better.
SGB is not a standalone answer and I do not present it as one. It works best as part of a plan that includes appropriate mental health care, and I want to know who else is involved in yours. The goal is to make other therapy more accessible, not to replace it.
Stellate ganglion block has a plausible mechanism grounded in autonomic physiology, a positive multisite randomized trial against sham, a meta-analysis that confirms a significant pooled effect, and a large clinical series showing anxiety scores roughly halved with most patients improving meaningfully. That is a stronger evidence base than most of what gets offered in wellness medicine, and considerably stronger than the field’s reputation suggests.
What it cannot promise is an individual response, and no honest clinician will quote you a personal success rate drawn from population data. Some patients get a great deal from this. Some get little.
What I can tell you is that if you have been carrying a nervous system stuck in a threat state, this is a real option with real evidence behind it, delivered in minutes, and increasingly well characterized. If you are considering stellate ganglion block in West Palm Beach, the right first step is an evaluation that establishes whether you are a good candidate and what we will measure to find out whether it helped.
The Evidence for Stellate Ganglion Block Has Caught Up With the Anecdotes
 What the Chelation Trials Actually Found, and Why Measurement Changes Everything
 Your Biological Age Test Is Less Precise Than You Think
 The Question About Regenerative Injections That Almost Nobody Asks
 What a Century of Blood Filtration Taught Me About Judging a New Therapy


